Azelaic Acid 10% vs 20%: Which Strength Is Better?
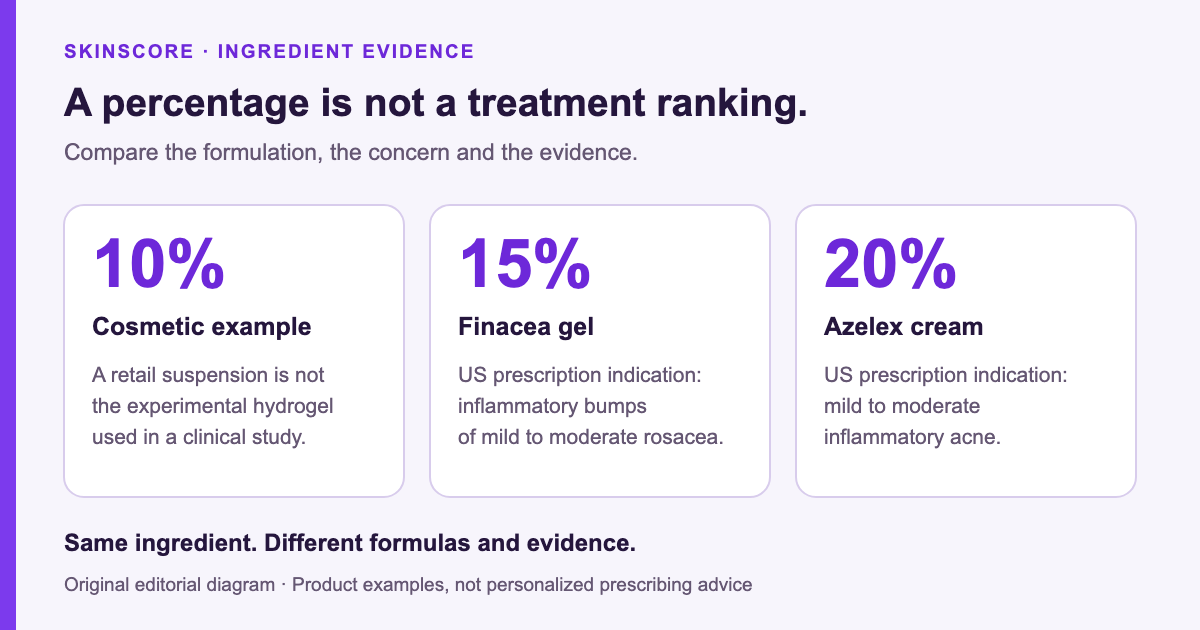
Azelaic acid 20% is not automatically better than 10%, and a 10% cosmetic is not automatically equivalent to a prescription product. Concentration tells you how much ingredient a formula contains. It does not establish how well that exact formula treats a particular condition, how your skin will tolerate it or whether it is the right treatment for you.
The missing middle matters too: 15% gel has a specific place in rosacea treatment. That does not make every 15% product a substitute for every 20% cream. This guide separates product labeling, clinical research and cosmetic claims so you can compare like with like. It is an editorial explanation of the evidence, not a diagnosis or a prescription schedule.
Contents
- The differences at a glance
- Is 20% azelaic acid too strong?
- What percentage of azelaic acid should you use?
- What a percentage does and does not tell you
- What the 10% versus 20% research actually tested
- Compare by concern, not just concentration
- Cosmetic products and prescription examples
- How to compare two products before switching
- Tolerability and the rest of your routine
- How to discuss results with a clinician
- Three example decisions
- Frequently asked questions
- Sources and editorial method
The differences at a glance
Use this table to identify the kind of comparison you are making. The medicine examples refer to US labeling; access, brand names and authorized uses can differ elsewhere. The cosmetic example identifies a real formulation, not a winner in a clinical comparison.
| Product example | What the number describes | What the evidence supports | What not to assume |
|---|---|---|---|
| The Ordinary Azelaic Acid Suspension 10% | A named 10% cosmetic suspension | Manufacturer information about that product and its cosmetic purpose | That trials of another 10% formula establish the same outcome |
| Finacea 15% gel | A particular azelaic acid medicine and vehicle | US indication for inflammatory papules and pustules of mild to moderate rosacea | That it treats every kind of facial redness or is simply a weaker 20% cream |
| Azelex 20% cream | A particular azelaic acid medicine and vehicle | US indication for mild to moderate inflammatory acne vulgaris | That twice the percentage means twice the benefit |
The relevant primary references are the Finacea prescribing information, Azelex labeling and The Ordinary's product page. None supplies a universal ranking of these three products against one another.
This is why the question “10 or 20, which is better?” needs a second question: better for which diagnosed concern, in which formulation, compared with what? A useful answer names those conditions rather than prescribing the same starting strength to everyone.
Is 20% azelaic acid too strong?
20% azelaic acid is not too strong by default: it is the strength of established prescription acne creams, and their labels describe irritation that is usually mild and temporary. It can be too strong for a particular person, routine or skin area, which is why the label and your response matter more than the number.
The official documents give a more reassuring and more nuanced picture than most forum threads. The FDA-approved Azelex 20% cream label reports pruritus, burning, stinging and tingling as the most common adverse reactions, each in approximately 1% to 5% of patients in its trials, and describes them as generally mild and transient. The same label links temporary irritation partly to the low pH of azelaic acid, especially when the cream is applied to broken or inflamed skin at the start of treatment.
The UK Skinoren 20% cream summary of product characteristics classes application site burning as very common, meaning it may affect at least 1 in 10 users. It also builds tolerance into the instructions: people with sensitive skin are advised to apply it once a day, in the evening, for the first week before moving to twice daily, and to reduce the amount or the frequency if irritation becomes intolerable. Follow the leaflet supplied with your own product, because instructions differ between brands and countries.
Why a lower percentage can still sting more
Percentage is a weak predictor of comfort. The Finacea 15% gel label lists burning, stinging or tingling in 29% of trial participants, pruritus in 11%, scaling or dry skin in 8% and erythema or irritation in 4%, typically during the first few weeks. Those figures are higher than the Azelex 20% figures above, even though the gel contains less azelaic acid.
That comparison does not prove that the gel is harsher. The trials enrolled different populations: people with rosacea, whose skin is often reactive, versus people with acne. They also used different vehicles, study designs and ways of recording side effects. The practical lesson is narrower and more useful: a 20% label is not a reliable sign that a product will hurt more, and a 15% or 10% label is not a guarantee of comfort.
Signs that 20% is too strong for you right now
- Burning or itching that keeps going well beyond the first minutes after application, or keeps getting worse over several days.
- Visible peeling, rawness or redness that was not there before you started.
- Discomfort that only appears since you added another active, such as a retinoid, benzoyl peroxide or an exfoliating acid, at the same time.
Any of these is a reason to pause and ask your prescriber or pharmacist rather than to push through. Swelling of the face, eyes or lips, or difficulty breathing, needs urgent medical attention. If you are trying a cosmetic azelaic acid product for the first time, our patch testing protocol explains how to test a small area before using it on the whole face.
What percentage of azelaic acid should you use?
The right azelaic acid percentage is the one studied and labeled for your concern: in the examples on this page, 20% cream for mild to moderate inflammatory acne, 15% gel for inflammatory rosacea bumps, and 10% cosmetics for people who want a nonprescription product for the look of uneven tone or blemishes. Your skin type, diagnosis and other treatments decide which of those questions applies to you.
| Your situation | Percentage you will usually meet | Question to ask first |
|---|---|---|
| You want a first, nonprescription product | 10% cosmetic | Does the brand state a purpose and directions for this exact formula? |
| You have diagnosed papulopustular rosacea | 15% gel (prescription example) | Does the indication match my bumps, or is my main concern redness alone? |
| You have mild to moderate inflammatory acne | 20% cream (prescription examples) | How should I start, and what should I do if it stings? |
| You have acne marks or melasma | Varies by study | Has the cause of the pigmentation been identified? |
Azelaic acid 10 vs 15 vs 20
Think of the three numbers as three different products rather than three steps on one ladder. Moving from 10% to 15% to 20% does not automatically add benefit, and the research summarized above does not show that a person must climb through them in order. Someone with acne may be prescribed 20% from the start, while someone with rosacea may be prescribed 15% and never need anything else. If acne is the concern, our adult acne routine shows where azelaic acid sits among the other evidence-based options.
What percent of azelaic acid is best for beginners?
For a beginner choosing on their own, a 10% cosmetic is the usual nonprescription option, simply because 15% and 20% medicines in the examples above require a prescription in the US. That is an access answer, not a ranking of results. For a beginner with diagnosed acne or rosacea, the best starting percentage is the one the clinician prescribes, often with a gentler start as described in the Skinoren leaflet. Our broader azelaic acid guide covers how it fits next to niacinamide, retinoids and sunscreen.
What is the highest percentage of azelaic acid?
Among the labeled medicines reviewed for this article, 20% is the highest strength: Azelex 20% cream in the US and Skinoren 20% cream in the UK. We did not find an established higher-strength medicine in the sources we checked. Treat any listing that promises a much higher percentage with caution, and ask a pharmacist what the product actually is before applying it.
What a percentage does and does not tell you
For a formula labeled by weight, 10% means 10 parts of the ingredient in 100 parts of the finished product; 20% means 20 parts. That arithmetic describes composition. It does not calculate an improvement in acne, a reduction in redness or the number of weeks until a mark fades.
A product is more than its headline active. The vehicle is the surrounding formulation that carries it: cream, gel, suspension or another delivery system. Products may also have different additional ingredients, instructions and evidence. Those differences make a simple comparison between two percentages incomplete.
An ingredient list is useful for identifying ingredients, but it is not a published clinical trial of the finished product. Nor does an attractive description such as “advanced delivery” prove superiority. When a manufacturer makes a performance claim, look for the actual study and check whether it tested the formula you are considering.
Avoid treating texture as a shortcut to potency. A cream is not automatically weak because it feels richer, and a gel is not automatically stronger because it feels lighter. The question is what is known about the particular formula, not which texture sounds more scientific.
Our SkinScore methodology explains the scope of our ingredient-based assessments. A catalog score cannot establish a medicine's suitability for you, reproduce a laboratory stability test or replace a comparison trial. We have not personally tested these strengths against each other, and this article does not claim a measured pH or absorption rate for products whose data are unavailable.
What the 10% versus 20% research actually tested
There is published direct research involving a 10% and a 20% formula, but an important detail often disappears when the result is repeated online. A 2021 randomized trial compared an experimental 10% azelaic acid nanocrystal hydrogel with a commercial 20% cream in mild to moderate acne. The treatment period was eight weeks. The authors reported improvement with both formulations and concluded that the experimental hydrogel was as effective as the cream in that study.
The 10% treatment was a specially developed nanocrystal hydrogel, not The Ordinary's suspension or a generic sample of all cosmetic 10% serums. The study therefore cannot establish that any product labeled 10% is equivalent to any product labeled 20%. It illustrates why the identity of the formulation matters when interpreting a percentage comparison.
The appropriate response to this result is neither “10% always wins” nor “10% has never been studied.” It is to ask whether the formulation, condition and study design match the claim being made. We did not find evidence in the sources reviewed for this article that establishes a universal winner across ordinary retail 10% cosmetics and prescription 20% creams.
Read a study in five steps
- Identify the product. Write down its full name, strength and vehicle. An ingredient name alone is not enough.
- Identify the participants. Were they being treated for acne, rosacea or a pigmentation concern? Those populations are not interchangeable.
- Identify the comparison. A trial against vehicle answers a different question from a trial against another active treatment.
- Identify the outcome. Fewer inflammatory lesions, an investigator score and a participant's satisfaction describe different results.
- Identify the duration and limits. A study at one follow-up point cannot tell you how every person will respond indefinitely.
Consider a hypothetical headline: “Lower strength works just as well.” Before applying it to your shopping decision, replace “lower strength” with the exact formula and “works” with the measured outcome. If the longer sentence no longer describes the products or concern you are comparing, the headline is not enough to guide that decision.
A result can be useful without settling every question. Research on a specific formulation helps explain its potential; it does not authorize a homemade dilution, prove that two products are interchangeable or tell you to change a prescribed treatment.
Compare by concern, not just concentration
Acne
Azelex's US indication concerns mild to moderate inflammatory acne. That is a product-specific medical use, not evidence that every person with an occasional spot should move to 20%. The NHS acne treatment guide describes azelaic acid as one option, including when benzoyl peroxide or topical retinoids cause particularly troublesome irritation. The choice sits within a broader treatment assessment.
If you are comparing products because breakouts continue, prepare a record of what you have used and how your skin responded. A clinician or pharmacist can help determine whether the issue is the treatment choice, tolerability or another factor. Increasing a percentage is only one possible change, and it is not a substitute for that assessment.
A cosmetic product's claim about the appearance of blemishes should not be treated as proof of equivalent treatment for diagnosed acne. Equally, the word “prescription” does not mean it is the right option for every individual. The comparison needs a defined goal and a product that is appropriate for that goal.
Rosacea
The Finacea gel indication is specifically about inflammatory papules and pustules. Its label states that effectiveness for rosacea redness without those lesions has not been evaluated. That distinction matters if your main concern is persistent flushing or color rather than bumps.
Instead of deciding that 20% must be the next step after 10%, ask whether your symptoms have been diagnosed and whether the treatment evidence matches them. Photographs and a symptom description can help an appointment, but an article cannot determine the cause of redness from the fact that a cosmetic stings.
We link our rosacea skincare guide for supporting routine context. It should be read alongside professional advice, not as a reason to substitute a cosmetic for a prescribed rosacea medicine. A stronger percentage alone does not answer a question about a different symptom.
Post-acne marks and other dark spots
Pigmentation research also needs careful labeling. A randomized study published in 2023 compared 20% azelaic acid cream with 5% topical tranexamic acid solution for acne-related postinflammatory hyperpigmentation. Thirty participants in each group completed the intervention. The study reported improvement in both groups, with more treatment-related side effects in the azelaic acid group at the first monthly assessment.
That was not a 10% versus 20% trial, and it does not establish a best percentage for every dark spot or for melasma. A claim about acne-related marks should stay attached to that concern. It should not be expanded into a promise that one strength will remove all pigmentation.
If you have not established what a mark is, choosing the biggest concentration is a poor substitute for finding out. Bring the question to a clinician rather than assuming that every patch belongs in the same product comparison. Once the concern is clear, our hyperpigmentation serum guide can provide additional product context without turning the catalog into a diagnosis.
Cosmetic products and prescription examples
The three percentages are often described online as a universal regulatory ladder: 10% cosmetic, 15% rosacea medicine, 20% acne medicine. That description combines familiar product examples with an overly broad rule. It should not be used to infer the legal status or authorized use of every product in every country.
For US shoppers, the medicine examples above have prescription labeling. A cosmetic sold without a prescription is a different kind of product, and its availability does not demonstrate equivalence to a medicine. If you are elsewhere, confirm the specific product with a local pharmacist and consult its local patient information rather than importing the US label's assumptions.
For a named cosmetic, inspect the current manufacturer's page and the packaging you actually receive. The Ordinary product analysis is a catalog reference to one 10% suspension, not a recommendation that everyone should start there. Check the manufacturer information if the formula, packaging or directions differ from an older description.
Keep three questions separate: can you buy it, what is it intended for, and what evidence supports that use? A product may be easy to order without answering the other two. Avoid using a marketplace listing or a concentration printed in large type as the only evidence for a treatment decision.
This article does not assess online sellers, quote current prices or recommend bypassing prescription requirements. It also does not assume that every international 20% listing is unlawful. Product status needs a product-specific and jurisdiction-specific check.
How to compare two products before switching
Make a short comparison sheet before buying another tube. It helps expose gaps that a list of “best strengths” can hide. Use the exact product names rather than describing both as “my azelaic acid,” especially if one contains additional active ingredients.
| Question | Product you already use | Product you are considering |
|---|---|---|
| Full name and concentration | Copy the label | Copy the label |
| Vehicle and other relevant ingredients | Record what is stated | Record what is stated |
| Intended use or authorized indication | Keep the wording specific | Keep the wording specific |
| Evidence for the actual formula | Link it, or write “not located” | Link it, or write “not located” |
| Instructions and access | Current label or prescription | Local label and access requirements |
| Your experience so far | Changes, discomfort and questions | Leave blank until there is actual experience |
“Not located” is an honest entry. It means you do not have a relevant study in front of you; it does not prove that no study exists. Similarly, your experience of a formula is relevant to your discussion with a professional, but it is not a trial demonstrating that everyone should choose the same concentration.
Compare costs without comparing treatment doses
If cost is part of your decision, compare the same units and include only expenses you can verify. A larger tube can have a lower price per gram while still being the wrong product for the intended use. Prescription access, pack size and the amount actually prescribed may also affect what you pay.
Do not calculate a “cost per effective percent” by dividing the price by 10 or 20. That arithmetic assumes clinical benefit rises in direct proportion to the ingredient percentage, which has not been established here. A price calculation can organize spending information; it cannot calculate a therapeutic advantage.
Tolerability and the rest of your routine
Azelaic acid is not irritation-proof. Burning, stinging, itching and dryness appear in medicine information. A lower number does not guarantee that a finished product will feel comfortable on your skin, and discomfort is not evidence that it is working better.
Follow the directions for your actual product and, for a medicine, your prescriber's instructions. This guide does not replace them with a universal pea-sized amount, alternate-night schedule or escalation timetable. If directions are unclear, ask the dispensing pharmacist or clinician to explain the amount, area of application and follow-up plan.
The Finacea label advises avoiding certain irritating products, including abrasive or peeling agents. Rather than adopting a blanket internet rule that every acid combination is forbidden or every combination is safe, bring your full routine to the discussion. Include nonprescription products: a prescription record alone will not show a scrub, exfoliating toner or serum you added separately.
Describe a reaction rather than naming it yourself
Write down the product used, when the reaction began, where it appeared and whether other products changed at the same time. “Stinging for a short time after application” and “persistent painful irritation” are different descriptions. Neither should automatically be called a normal adjustment or “purging.”
For severe or persistent irritation, stop using the product and obtain medical advice. Facial swelling or difficulty breathing warrants urgent medical attention. These symptoms are described in the Finacea safety information; the full product leaflet remains the reference for precautions, including eye contact and other warnings relevant to that medicine.
A photo under ordinary lighting may help you explain what happened. Do not use filters or compare one image taken in bright daylight with another taken under a warm lamp as if it were a measured treatment result. If symptoms are concerning, getting advice matters more than completing a photo diary.
Pregnancy and breastfeeding questions
The American Academy of Dermatology's pregnancy guidance describes azelaic acid as thought to be safe during pregnancy. That wording is not an instruction to choose a strength or start a new regimen without discussing your situation. Ask your obstetric clinician or dermatologist about the exact formula, and raise breastfeeding separately if relevant.
How to discuss results with a clinician
An agreed review point is more useful than a universal promise that every strength works in the same number of weeks. The NHS notes that acne treatment can take months, while some improvement with azelaic acid may appear earlier. Individual response and the condition being treated still matter. Do not turn one trial's eight-week endpoint into a deadline for changing your own prescription.
Before an appointment, collect a short record rather than a long list of guesses. Include the product name, the instructions you followed, approximate start date, missed use if relevant, unwanted effects and any other changes in the routine. The purpose is to make the history understandable, not to grade your consistency.
Useful questions include:
- What condition are we treating, and which change should we monitor?
- Does the evidence concern this exact product or a different formulation?
- What should I do if I experience irritation?
- When should we review the result, and what would justify a different plan?
- Which of my existing skincare products should I discuss before continuing?
If a product has not met your expectations, the next decision need not be a higher percentage. It may be a review of the diagnosis, expectations or treatment approach. A comparison guide can help you ask better questions without deciding the answer in advance.
Three example decisions
These are fictional situations showing how to organize information, not treatment plans or patient testimonials.
A cosmetic shopper sees “twice the strength.” They currently use a 10% product for the appearance of uneven tone and find a 20% listing. The useful next step is to identify the new product, its intended use and local status. There is no evidence in the advertisement's percentage alone that it will deliver twice the improvement. The comparison sheet remains incomplete until those details are known.
A person with diagnosed rosacea wonders why their prescription says 15%. The percentage looks lower than a 20% cream discussed online. They check the actual indication and ask the prescriber why that formulation was selected. This avoids treating medicine selection as a competition between numbers and keeps the question tied to their diagnosed symptoms.
Someone finds a paper saying 10% performed well against 20%. They first identify the experimental nanocrystal hydrogel, then compare that name with their retail product. The mismatch prevents them from applying the study directly to their own tube. The paper remains informative about formulation research without becoming proof of equivalence for a different cosmetic.
In each example, better information changes the question before any purchase or treatment change. That is the practical purpose of comparing strengths carefully.
Frequently asked questions
Is 20% azelaic acid better than 10%?
Not universally. A meaningful comparison needs the actual formulation, condition and outcome. A study of an experimental 10% nanocrystal hydrogel cannot establish that all retail 10% products equal a 20% cream. Discuss treatment changes with a clinician rather than choosing by percentage alone.
Is 20 percent azelaic acid too much for sensitive skin?
Not necessarily, but sensitive skin deserves a slower start. The UK Skinoren 20% leaflet advises once-daily evening use for the first week in people with sensitive skin before moving to twice daily. If burning persists or worsens, reduce use and ask your prescriber or pharmacist rather than pushing through.
Does 20% azelaic acid sting more than 15%?
Not reliably. In the US labels, burning, stinging or tingling was reported by 29% of Finacea 15% gel trial participants, against approximately 1% to 5% for Azelex 20% cream. The trials differed in population and design, so these numbers show that percentage does not predict comfort, not that one product is gentler.
What is the highest percentage of azelaic acid available?
In the labeled medicines reviewed here, 20% is the highest strength, found in Azelex cream in the US and Skinoren cream in the UK. The cosmetic example on this page, The Ordinary's suspension, is 10%. Be cautious with any listing claiming a much higher concentration and check what it is with a pharmacist.
Why is 15% gel used when 20% cream exists?
They are different formulations with different product-specific evidence and labeling. In the US examples discussed here, Finacea 15% gel is indicated for inflammatory rosacea bumps, while Azelex 20% cream is indicated for mild to moderate inflammatory acne. The lower percentage does not make the gel an inferior version of the cream.
Is 10% enough for dark spots?
The number alone cannot answer that question. The studies cited here do not establish one best concentration for every pigmentation concern or prove that a cosmetic 10% formula is equivalent to a medicine. Identify the concern and assess the specific product instead of treating all dark spots as the same problem.
Can I buy 20% without a prescription?
Check the specific product and your country. Azelex 20% cream has prescription labeling in the US, but this does not establish the status of every 20% product worldwide. A pharmacist can clarify local access and whether the product you found is appropriate to discuss as a treatment option.
Can I mix 20% with moisturizer to make 10%?
Do not treat a homemade mixture as an equivalent, tested 10% product. Changing a finished formula introduces uncertainties that a simple percentage calculation does not resolve. Use products as directed and ask your pharmacist or prescriber before modifying a medicine.
Can I use azelaic acid with retinol or exfoliating acids?
There is no single schedule that applies to every combination. Product instructions, your skin's response and any prescription plan matter. Show the complete routine to your clinician or pharmacist, particularly if you have irritation, and avoid assuming that a “gentle” ingredient makes every combination suitable.
How long should I wait before changing strength?
Agree on a review plan for the actual condition and product. Research follow-up periods are not universal deadlines, and persistent irritation should not be ignored while waiting for a calendar date. Record your experience and seek advice rather than automatically moving from 10% to 20%.
Sources and editorial method
SkinScore Editorial reviewed this page on November 2, 2026. Its original publication date is retained. The September 2026 update replaced broad strength recommendations with product-specific labeling, two primary clinical studies and practical comparison questions. The November 2026 update adds a direct answer on whether 20% is too strong, label-reported tolerability figures for Azelex 20% cream and Finacea 15% gel, the Skinoren 20% start-up instructions and a percentage guide by concern. No dermatologist review or first-hand product test is claimed.
The external references linked above comprise US medicine labels on DailyMed and on the FDA's Drugs@FDA site, the UK Skinoren summary of product characteristics, two original trials, NHS patient information, AAD pregnancy guidance and a manufacturer's cosmetic product page. For the ingredient itself, see our azelaic acid ingredient profile. The manufacturer is cited for product identity, not as independent comparative evidence. Clinical findings are kept attached to their studied formulation and condition; the tables and fictional scenarios are original editorial aids.
Your next step: complete the comparison sheet with the products you are actually considering. For a medical concern or a prescribed treatment, take that information to your clinician or pharmacist before changing the plan.
Enjoyed this? Share it